
Office Phone Number: (832) 644-8930
New Patient Appointments: (346) 662-1220
The Role of Geography and Race in Cardiovascular Disease
Research reveals that where you live may affect your chances of dying from a stroke or heart disease.
There are still hot spots nationwide where these mortality rates are unusually high. Poverty and lack of access to quality care can condemn many Americans to an early death.
Two main factors appear to be driving the differences in cardiovascular disease risks.
One is exposure to risks that cause stroke and cardiovascular diseases, such as high blood pressure, poor diet, high cholesterol, obesity, and smoking. The other is the lack of access to good primary and hospital care.
To estimate death rates from cardiovascular disease, researchers selected death records from more than three thousand and one hundred counties in the United States.
The death rate from cardiovascular disease declined by fifty percent between 1980 and 2014, from 507 deaths per 100,000 individuals to 253 deaths per 100,000 individuals.
Nevertheless, across the country, substantial differences between counties were evident. Significant differences also existed for heart failure, artery and vein disease, atrial fibrillation, and other heart-related conditions.
The counties with the highest death rates from cardiovascular disease were in a swath extending from Southeastern Oklahoma along the Mississippi River valley to eastern Kentucky.
Outside the South, several clusters in which cardiovascular disease rates were high included the following:
You can find the lowest death rates from cardiovascular disease in counties around San Francisco and central Colorado, northern Nebraska, central Minnesota, northeastern Virginia, and southern Florida.

Even in states where individuals think they are relatively healthy, you can still find places where individuals are unhealthy.
Hopefully, we may use these data to identify areas where mortality rates are high and improve health care and lifestyle interventions to reduce deaths from cardiovascular disease.
The above research should remind us of the crucial role that social aspects play in health, including environment, educational factors, and social and economic status.
Disparities between counties are likely due to the prevalence of risk factors and differences in access to quality care.
Decreasing death rates from heart attack and stroke in the United States may obscure many essential details about who benefits and who does not benefit from such trends.

Heart disease is the primary cause of death for adults in the United States. Yet, it affects some individuals, especially minority groups, more strongly than others. For example, healthcare providers diagnosed 47% of black adults compared to 36% of white adults.
Regarding cardiovascular disease risk factors, racial and ethnic minority groups bear a heavier burden. For example, Hispanic women are twice as likely as white women to have diabetes, a significant risk factor for heart disease. In addition, American Indians are three times more likely than white people to have diabetes.
Risk factors and diagnoses of cardiovascular disease are more frequent among ethnic minorities. Social factors, known as “social determinants of health,” drive these health disparities.
Health inequalities or disparities exist because of differences between racial and ethnic groups. These inequalities are a complex and challenging problem in the United States and worldwide.
Researchers view race and ethnicity as social constructions rather than biological traits, meaning that genetics do not cause health differences between racial and ethnic groups. Instead, social factors play the most significant role in shaping an individual’s health.
Many social factors affect an individual’s health. Some crucial factors include an individual’s ability to access the following:
These factors, which are the “social determinants of health,” connect. For example, poverty can prevent individuals from eating a heart-healthy diet. Likewise, if those individuals live without healthy food choices, their options are even more limited.
Unfortunately, social factors disadvantage blacks, Hispanics, and American Indians. These groups frequently bear a heavier economic and social burden. As a result, their health also suffers. Other groups also face disadvantages that affect their risk of cardiovascular disease.

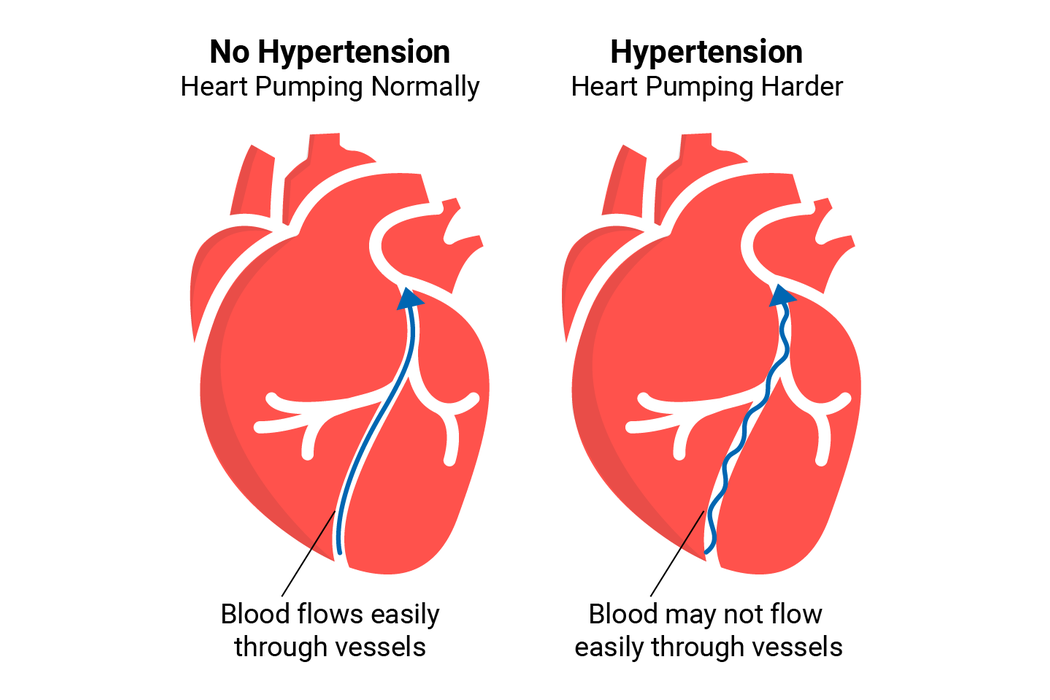
Hypertension (high blood pressure) and type 2 diabetes affect certain racial and ethnic groups in the United States, the two major risk factors for cardiovascular disease.
–HYPERTENSION OR HIGH BLOOD PRESSURE
Social factors impact these numbers. For example, individuals who do not have insurance are more prone to uncontrolled hypertension. In addition, individuals who face discrimination suffer from higher blood pressure.
Hypertension (high blood pressure) may lead to complications, including the following:
–TYPE 2 DIABETES
Type 2 diabetes may damage blood vessels in the heart, kidneys, and brain. This condition also causes triglyceride and LDL cholesterol levels to rise. As a result, individuals with diabetes are twice as prone as those without diabetes to have a stroke or heart attack.
Approximately one in ten individuals in the United States has diabetes, and ninety to ninety-five percent suffer from type 2 diabetes. Diabetes is an urgent health crisis for all individuals. Yet, it affects some racial and ethnic groups more frequently.
Some researchers identify diabetes as an exemplary disease of health inequality. That is, differences between racial and ethnic groups are evident in the data. And social factors drive them. For example, some racial and ethnic disparities in diabetes prevalence include the following:
ETHNIC GROUP WITH THE HIGHEST RATE OF CARDIOVASCULAR DISEASE
Heart disease rates fluctuate depending on the specific diagnosis. Next are some insights from research in the United States.
–HEART FAILURE
–HEART ATTACK AND CORONARY ARTERY DISEASE
–STROKE
Some individuals face higher risks than others. For example, if you belong to a racial or ethnic group confronting health inequity, talk to your healthcare provider about your threats and options. In addition, it is essential to start young with checkups, getting your blood pressure, blood sugar, and cholesterol numbers.
You and your healthcare provider may work together to identify your risks and find ways to reduce them.
We are Modern Heart and Vascular Institute, a diagnostic and preventative medicine cardiology practice. For more information, contact us.

CARDIOVASCULAR CENTERS IN HOUSTON, TEXAS
Modern Heart and Vascular, a preventive cardiology medical practice, has several offices around Houston. We have locations in Humble, Cleveland, The Woodlands, Katy, and Livingston.
We are Modern Heart and Vascular Institute, a diagnostic and preventative medicine cardiology practice.
Every heart has a story… What’s yours?
Book an Appointment Today
At the Modern Heart and Vascular Institute, we offer state-of-the-art cardiovascular care with innovative diagnostic tools and compassionate patient care. Our priority at Modern Heart and Vascular Institute is prevention. We help patients lead healthier lives by avoiding unnecessary procedures and surgeries.
Contact us online to learn more and book an appointment. If you’d like to learn more about our practice, read our providers’ bios.
This article does not provide medical advice. It is intended for informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you need cardiovascular care, please call us at 832-644-8930.
Every heart has a story…What’s yours?
Choose your appointment at one of our 7 locations